The question
Why do acne scars behave differently from active acne — and why does the studio refuse to treat them as one “acne pathway” in language?
What is happening biologically?
Active acne is an inflammatory process in the follicle and surrounding tissue: congestion, bacteria, immune response, sometimes cystic depth. The skin environment is reactive. Needling through active inflammatory lesions can worsen injury, spread inflammation, or simply be the wrong tool.
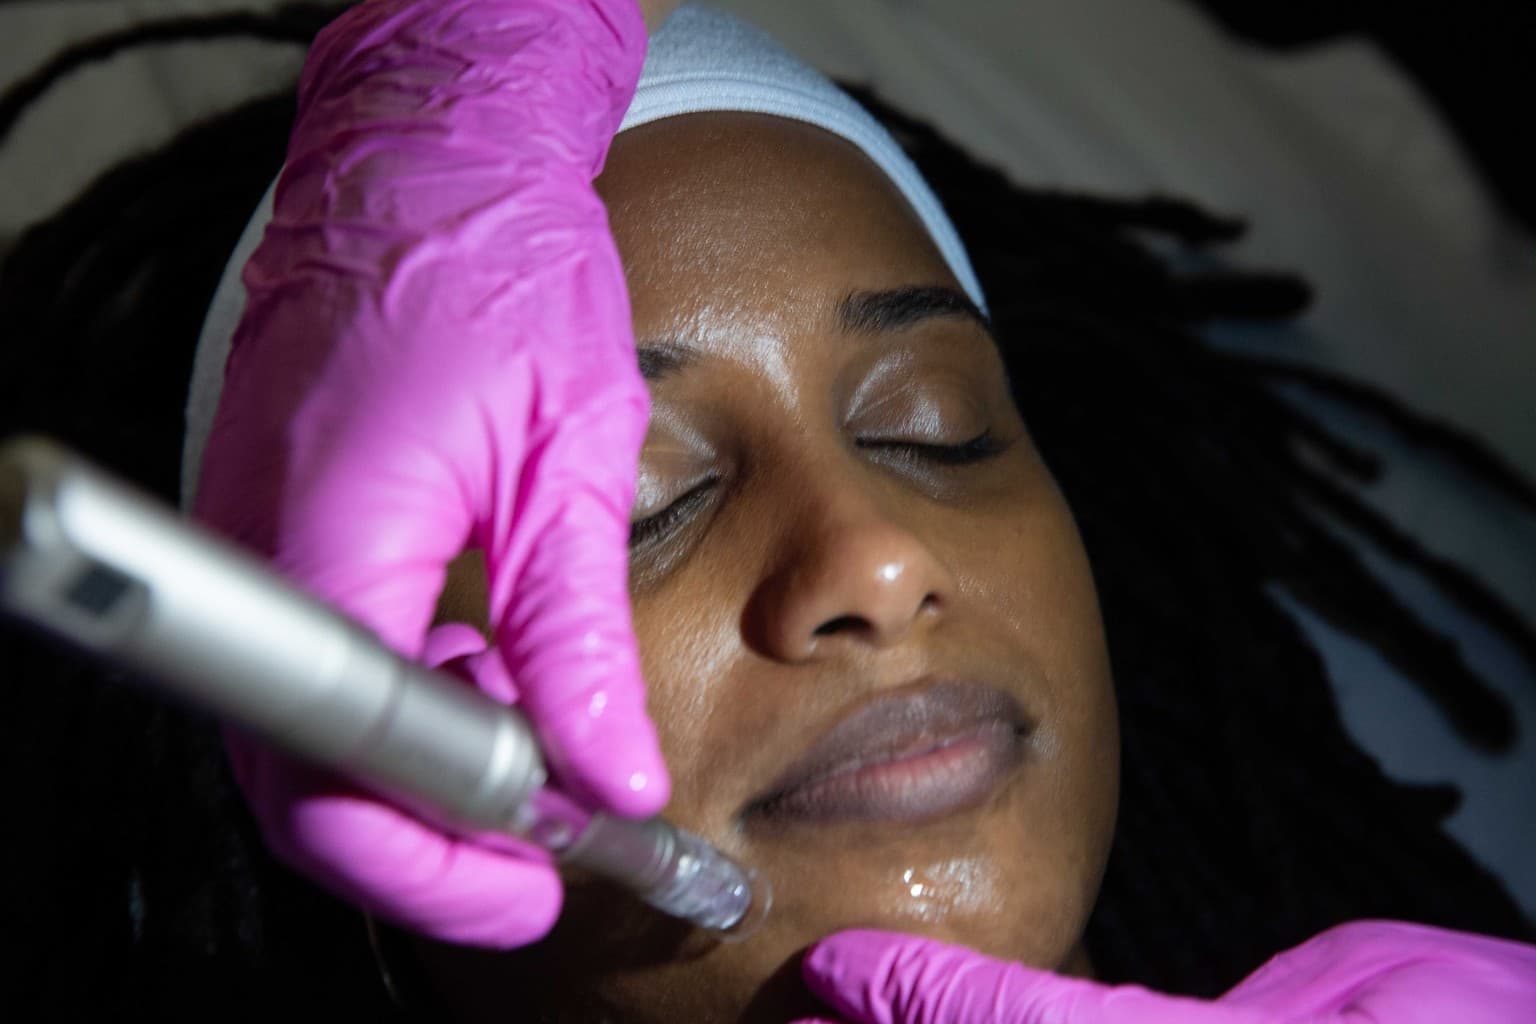
Acne scarring is later architecture — atrophic wells, tethering, uneven collagen — after inflammation has already remodeled poorly. The clinical question becomes whether controlled remodeling can reorganize that structure over time.
Those are different tissues in different chapters. Restore is the language for active breakouts and the environment around them. Refine is the language for scar remodeling. One person can need both — sequentially. That is still two intentions.
What research has studied
How we use numbers. When a percentage or count appears here, it belongs to a named study with a named population. It is not a studio guarantee.
Microneedling literature more often addresses atrophic scarring and texture than the clearing of active inflammatory acne (Alster and Graham, 2018). We do not publish claims that needling “clears” active acne, and we do not treat a scar paper as a license to needle inflamed lesions.
In 39 patients with Fitzpatrick types III–V and pigmented acne scarring, microneedling was associated with statistically significant improvement on both a post-acne hyperpigmentation index and a Goodman–Baron scar scale, without worsening of pigmentation in that cohort (Al Qarqaz and Al-Yousef, 2018). That supports cautious scar-and-pigment work in darker skin tones. It is not a 60% PIH-reduction figure, and it is not a study of active cystic acne.
What this means in practice
Assessment may find that active acne needs stabilization, medical collaboration, or a quieter plan before any collagen-induction work. When surrounding tissue is considered, it is because the environment can use support — not because we are rolling over open lesions.
Scar work, when appropriate, is paced and photographed over a pathway. Pigment that sits with scarring is assessed as its own risk, especially in skin of color.
Federica’s clinical perspective
I have watched patients arrive hoping a single pass will both quiet breakouts and lift old scars. Biology rarely offers that bargain. My job is to say which chapter we are in, and to protect the tissue from a stimulus it cannot use yet.
Surrounding-tissue care, barrier support, and sometimes adjunctive light belong in Restore when they help the environment. Refine begins when the architecture, not the flare, is the problem we are asking collagen to meet.
Related pathways
Those are two chapters, not one package. Active Acne is Restore. Acne Scar Remodeling is Refine. Both still sit behind one clinical gate: Online Assessment, review, and consultation before any treatment intensity is set.
The next step is not a retail booking. Begin with the Online Assessment so Federica can review what the skin is actually asking for.
Educational only — not a substitute for personalized medical advice. Talk with a qualified clinician about your own care.
Visual explanation
Needle depth is a clinical choice about which layer is being asked to respond — not a retail setting. Thickness varies by face zone, age, and how much pressure is applied.
Last reviewed 2026-08-18 · Practitioner perspective


